











Short answer
Both are specialty implants for an upper jaw that has lost too much bone for standard implants. Zygomatic implants anchor in the cheekbone and are used for severe bone loss. Pterygoid implants anchor in the pterygoid plate, dense bone at the back of the upper jaw, and suit loss toward the back. A 3D scan shows which one, or both, your anatomy can support.
What is the difference between a zygomatic implant and a pterygoid implant?
The difference is where each one anchors. A zygomatic implant is a long implant that passes through the upper jaw, inside or alongside the sinus, and engages the cheekbone. A pterygoid implant is angled into the pterygoid plate, dense bone behind the last upper molar position. Both anchor in bone that standard implants do not use, and each is placed alongside other implants to carry a fixed arch.
Both exist because of what happens after upper teeth are lost. The ridge that held them shrinks, and the sinus above the back teeth can enlarge into the space. A 2024 systematic review in the Journal of Clinical Medicine describes bone in the back of the upper jaw as typically low in density with a thin outer layer, and notes that the sinus often limits what is left. A standard implant then has little to hold.
Zygomatic implants solve this by reaching up into the cheekbone. Pterygoid implants solve it by reaching back into the pterygoid plate. Neither is the automatic answer. A 2023 systematic review of indications found that the main reason for zygomatic implants was extreme upper jaw bone atrophy, and that the studies did not define 'extreme' the same way. That is why the choice is made on your own 3D scan, not from a rule of thumb.
| Zygomatic implant | Pterygoid implant | |
|---|---|---|
| Anchors in | The cheekbone | The pterygoid plate, behind the upper molars |
| Bone loss it suits | Severe loss across the upper jaw | Loss toward the back of the upper jaw |
| Usually placed with | Standard implants at the front, or a second zygomatic implant on each side (quad zygoma) | Implants elsewhere in the same arch, sometimes zygomatic ones |
| Survival in separate systematic reviews (not a head-to-head comparison) | 96.2% at 6 years (2023) | 92.5% at 10 years to 97.9% pooled, depending on the review (2024, 2026) |
| Main reported downside | Sinusitis | Difficult surgical access |
What are zygomatic implants?
Zygomatic implants are much longer dental implants that anchor in the zygomatic bone, your cheekbone, instead of the upper jawbone. A Cochrane review describes them as about 3 to 5 cm long, against 0.5 to 2 cm for standard implants. They are used when the upper jaw has shrunk too much to hold standard implants securely.
They usually support a fixed arch rather than a removable denture. The Cochrane review notes that fixed teeth can often be fitted much sooner because grafting is avoided. At ANEWU, qualifying cases, not all of them, can receive a fixed temporary (provisional) bridge soon after surgery, and the final bridge follows once the implants have healed.
Not every jaw is suited to them. The cheekbone has to be sound enough to carry the arch, and a 3D scan confirms that. At ANEWU, Dr. Abtin Shahriari plans and performs zygomatic cases, and the scan is taken at the free consultation. The scan can also rule zygomatic implants out, in which case grafting or pterygoid implants may be the better fit.
What are pterygoid implants?
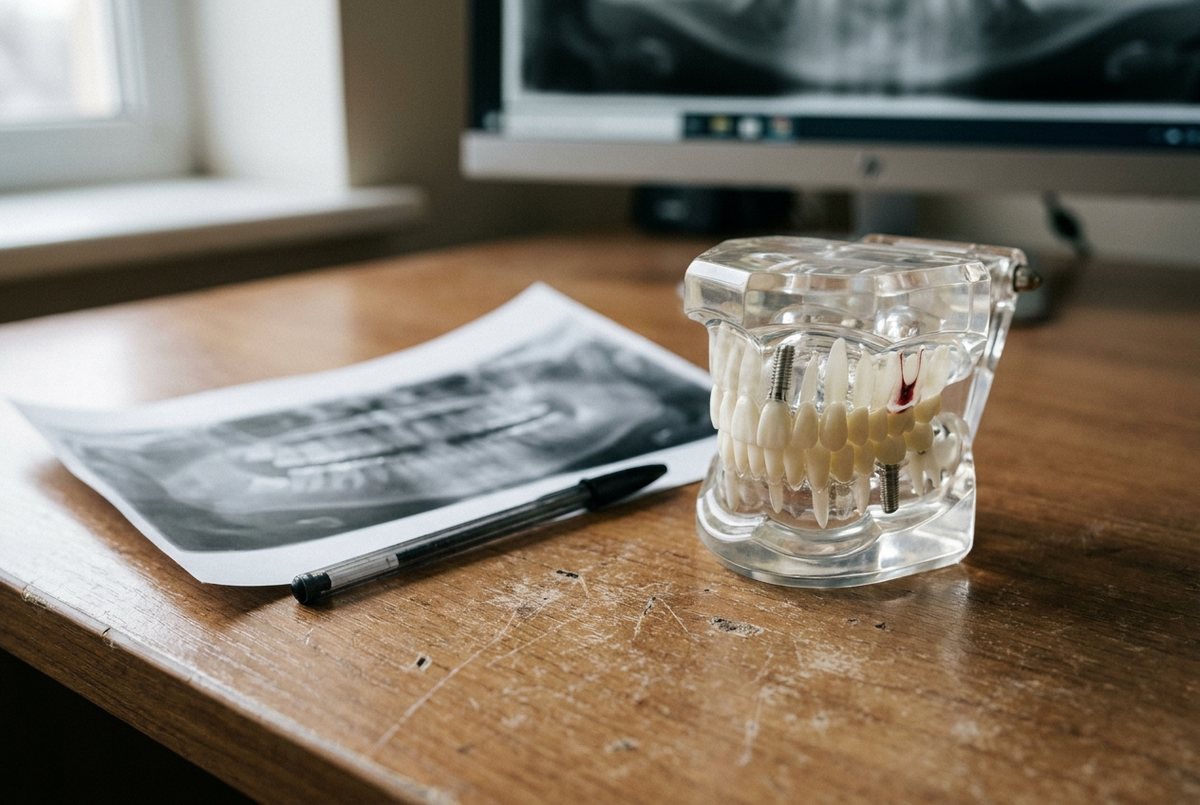
Pterygoid implants are dental implants placed at an angle into the pterygoid plate, dense bone at the back of the upper jaw. They give patients with limited bone in the usual implant sites a fixed-arch option that often avoids a separate bone graft. They are usually combined with implants placed elsewhere in the same arch.
A 2026 systematic review in Clinical Implant Dentistry and Related Research calls them a graftless option for posterior maxillary atrophy, engaging the dense cortical bone of the pterygomaxillary complex. A 2024 review describes this anchorage as working without sinus augmentation or supplemental grafting. Of the 3,053 pterygoid implants in that review, 75.0% supported a fixed full-arch prosthesis.
The same 2024 review lists cases where the technique may not suit: too little bone in the tuberosity area, impacted third molars, or limited mouth opening. It is a more specialized approach than a routine implant, used for specific patterns of bone loss rather than as a default. At ANEWU, Dr. Abtin Shahriari plans and places pterygoid implants from a 3D scan.
How successful are zygomatic implants, and how long do they last?
A 2023 systematic review of 18 studies found a mean survival of 96.2% at 6 years across 1,349 zygomatic implants in 623 patients, with a mean follow-up of 75.4 months. The authors concluded that long-term survival is comparable to conventional implants. Longer-term comparisons are still lacking, so no one can promise a number of years.
Other evidence agrees. A 2025 meta-analysis of 15 studies, limited to zygomatic implants placed outside the sinus (the externalized technique), reported a 96.7% success rate for 1,555 zygomatic implants against 97.9% for 1,865 conventional implants, though only three of its 15 studies had a low risk of bias. In the 2023 review, the yearly failure rate was 0.7%, higher in the first year (2%) than afterward (0.5% a year), and the prostheses the implants supported had a mean survival of 94%.
Two cautions apply. The evidence is not strong: the 2023 authors note that no randomized trials were included, and Cochrane rated its confidence in the comparison with grafting as very low to moderate. And survival only counts implants that stayed in. It says nothing about how often something needs attention, which is what the next section covers.
What are the disadvantages of zygomatic implants?
The main disadvantages are a more complex surgery, more complications than standard implants in grafted bone, and sinusitis. In a 2023 meta-analysis, sinusitis had a pooled prevalence of 14.2% over a mean follow-up of 65.4 months and was the most commonly reported factor linked to implant loss. Many cases responded to treatment, but some needed the implant removed.
The rate may depend on the technique. A 2025 meta-analysis of zygomatic implants placed outside the sinus reported sinusitis in 3.0% of 803 patients and infections in 1.6%. Direct comparisons between techniques are limited, so treat the gap as a reason to ask your surgeon which path is planned for your jaw, not as a promise. At ANEWU, Dr. Abtin sets the path, angle and depth of each implant against your own anatomy.
Compared with building up the jaw first, the 2026 Cochrane review judged that cheekbone implants probably led to more complications, based on one small study of 71 people followed for three years: roughly four-fifths of people with them had complications, against about half with standard implants in grafted bone. The same review found they probably failed less often and allowed teeth to be fitted much sooner. A 2021 cadaver study notes that the implant's length and its closeness to vessels, nerves and the eye socket make this procedure challenging, which is why it asks more of the surgeon and the planning.
What is the average survival rate for pterygoid implants?
Systematic reviews report survival for pterygoid implants between 92.5% and 97.9%, depending on the studies and follow-up counted. A 2026 meta-analysis in Clinical Implant Dentistry and Related Research pooled 97.9%, while a 2024 review estimated 92.5% cumulative survival at 10 years. Most failures happen in the first year, and the certainty of the evidence is low to very low.
Why the spread? The reviews pool different studies, follow-up lengths and implant surfaces, and many of the underlying studies are retrospective. The 2023 review of modern roughened-surface implants found 39 failures among 911 implants over 6 years, and 37 of those happened in the first year, 30 of them before the implants were loaded. If a pterygoid implant is going to fail, it usually does so early.
Implants joined to others in a fixed bridge fared better. The 2024 review found that non-splinted implants, such as single crowns and overdentures, had higher failure rates. That helps explain why pterygoid implants usually form part of a full arch rather than standing alone.
| Review | Studies and implants | Reported survival |
|---|---|---|
| 2026, Clinical Implant Dentistry and Related Research | 17 studies, 1,915 pterygoid implants (survival pooled from 14) | 97.9% pooled (certainty low to very low) |
| 2026, International Journal of Oral and Maxillofacial Surgery | 6 studies, 904 pterygoid and 2,940 conventional implants | 95.25% pterygoid vs 97.88% conventional |
| 2024, Journal of Clinical Medicine | 38 studies (pterygoid and tuberosity), 3,053 pterygoid implants | 92.5% at 10 years (mean follow-up 61.0 months) |
| 2023, Journal of Prosthodontics | 10 studies, 911 roughened-surface implants | 95.5% at 6 years |
What are the downsides of pterygoid implants?
Pterygoid implants have a somewhat lower survival rate than standard implants, a harder surgical approach and a thinner evidence base. A 2026 meta-analysis of full-arch cases found pterygoid implants survived at 95.25% against 97.88% for conventional implants, a significantly higher risk of loss (risk ratio 1.54).
Reported complications are uncommon but real. The 2024 review lists an implant displaced into the pterygoid fossa, sinus membrane perforation, sinusitis, severe postoperative pain, bleeding, and reduced sensation in the palate that lasted 4 weeks. A separate 2026 meta-analysis in Clinical Implant Dentistry and Related Research described complications as infrequent but inconsistently reported.
The evidence is also thinner than for standard implants. The 2026 comparison pooled six studies, three at high risk of bias, and only one measured marginal bone loss, finding similar values (0.64 to 0.68 mm for pterygoid, 0.61 to 0.62 mm for conventional). The 2024 review adds that this part of the jaw is hard to reach and has poor bone quality, which can matter more to survival than implant length.
How do you know whether you need zygomatic implants, pterygoid implants or a bone graft?
A 3D cone beam scan decides. It shows how much bone is left in height and width, where the sinus sits, and whether the cheekbone and the back of the jaw can carry implants. From that, your surgeon can say whether grafting, zygomatic implants, pterygoid implants or a combination fits your jaw. Where enough bone remains, the specialty techniques are usually not needed.
Use these rules as a guide, not a diagnosis. Moderate bone loss often suits bone grafting followed by standard implants, which keeps future options open but adds months of healing, and Cochrane notes grafting may take more than a year before replacement teeth are fitted. Severe loss across the upper jaw points toward zygomatic implants. Loss concentrated at the back points toward pterygoid implants, often with other implants in front. If enough bone remains in the jaw, a fixed arch on All-On-4, All-On-6 or All-On-X implants placed in the jaw is usually used instead.
Planning matters for both. In a 2021 cadaver study of one custom guided system (40 zygomatic and 20 pterygoid implants in 10 cadavers), planned and placed positions differed by a mean of 1.69 degrees for zygomatic implants and 4.15 degrees for pterygoid implants. That is a lab study of one system, not a measure of results in patients. At ANEWU, your 3D scan is taken at the free consultation and reviewed with you on screen, and a second opinion built on a 3D scan can reach a different conclusion than one built on a flat x-ray. If you were told you do not have enough bone, you can book a consultation at the Buckhead, Cumming or Dawsonville office to have your own scan read.
Sources and further reading
- Interventions for replacing missing teeth: zygomatic implants for the rehabilitation of the severely atrophic edentulous maxilla Cochrane Database of Systematic Reviews, 2026
- Long-term treatment outcomes with zygomatic implants: a systematic review and meta-analysis International Journal of Implant Dentistry, 2023
- Effectiveness of zygomatic implants using the externalized technique in the rehabilitation of atrophic maxillae: a systematic review with meta-analysis Medicina Oral, Patologia Oral y Cirugia Bucal, 2025
- Indications for zygomatic implants: a systematic review International Journal of Implant Dentistry, 2023
- Clinical Outcomes of Pterygoid and Maxillary Tuberosity Implants: A Systematic Review Journal of Clinical Medicine, 2024
- Indications, Techniques and Complications Associated With Pterygoid Implants: A Systematic Review and Meta-Analysis Clinical Implant Dentistry and Related Research, 2026
- Effectiveness of pterygoid dental implants in the complete arch rehabilitation of the edentulous maxilla: a systematic review and meta-analysis International Journal of Oral and Maxillofacial Surgery, 2026
- Implants in the pterygoid region: An updated systematic review of modern roughened surface implants Journal of Prosthodontics, 2023
- Impact of Osteoporosis on Dental Implant Survival, Failure, and Marginal Bone Loss: A Systematic Review and Meta-Analysis Journal of Clinical Medicine, 2025
- Dental Implant Failure and Medication-Related Osteonecrosis of the Jaw Related to Dental Implants in Patients Taking Antiresorptive Therapy for Osteoporosis: A Systematic Review and Meta-Analysis Endocrine Practice, 2025
- A Novel Guided Zygomatic and Pterygoid Implant Surgery System: A Human Cadaver Study on Accuracy International Journal of Environmental Research and Public Health, 2021
This article is general information about dental and facial procedures, not a diagnosis or medical advice. Every jaw and every health history is different, so the right plan for you can only be set after an exam and imaging with a surgeon.